
Quick answer
Standard deep brain stimulation for Parkinson's disease targets the subthalamic nucleus at high frequency. It controls tremor, rigidity and slowness well — and does poorly with freezing of gait, the symptom that causes falls and loss of independence, affecting more than 80% of patients in advanced disease. Lowering the frequency helps the gait and worsens the limbs. Li Jianyu and colleagues at Xuanwu Hospital tested a way out: stimulate the subthalamic nucleus at high frequency and the substantia nigra pars reticulata at 30 Hz simultaneously, using an eight-contact directional electrode. Both freezing and limb symptoms improved [1][2][4].
Key takeaways
- Design: multicentre, prospective, single-blind study, published 19 January 2026 [1][4].
- Stimulation: subthalamic nucleus at 130–210 Hz, substantia nigra pars reticulata at 30 Hz [3].
- Hardware: an eight-contact directional electrode allowing independent parameters on one lead [3][5].
- Contact plan: three contacts in the nigra, three in the subthalamic nucleus, two in the zona incerta [3].
- Outcome: significant improvement in freezing of gait together with motor symptoms [1][2].
Why one target was not enough
Freezing of gait is not simply a dopamine problem. It involves the basal ganglia loop that standard stimulation addresses, but also cerebellar-brainstem gait networks that it does not. The reasoning behind dual-frequency stimulation is that the two circuits need different treatment: high frequency for the limb circuit, low frequency for the gait circuit, delivered at the same time [4][5].
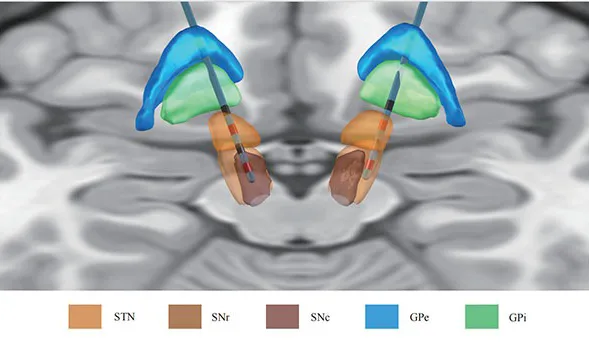
The eight-contact lead is what makes it physically possible: a conventional four-contact electrode cannot cover both nuclei with independently programmable parameters. Target localisation uses preoperative 3T MRI fused with postoperative CT to identify the dorsal nigra region associated with freezing [5].
How strong is the evidence
A prospective multicentre single-blind design is a reasonable step for a device strategy that requires surgical implantation, and the reported improvement in both domains addresses the trade-off that made earlier low-frequency approaches unsatisfactory [1][4].
Patients knew which settings they received, which matters for a symptom as suggestible as gait. Freezing is also episodic and hard to measure: laboratory gait tasks correlate imperfectly with freezing at home, and the study's follow-up duration is not reported in the summaries available. Programming a dual-target, dual-frequency configuration is more complex than conventional DBS, so results depend on programmer expertise. A separate double-blind randomised crossover trial comparing dual-target with single-target stimulation is registered and recruiting [1][5].
The condition in context: freezing of gait
Freezing is brief, unpredictable and the commonest reason an otherwise mobile patient falls.
| Region | What the data shows | Source |
|---|---|---|
| Prevalence | Affects more than 80% of patients with advanced Parkinson's disease [1]. | Xuanwu Hospital [1] |
| Standard DBS | High-frequency subthalamic stimulation improves limbs but has limited effect on freezing and may induce it [4]. | Kangxun [4] |
| Prior attempts | Low-frequency subthalamic stimulation helps gait but can cause rebound of limb symptoms [1]. | Xuanwu Hospital [1] |
Because freezing, not tremor, determines whether a patient can walk unaided, closing this gap changes independence rather than symptom scores [2].
Why it matters
| Potential | What the report suggests | Source |
|---|---|---|
| Both domains | Limb symptoms and freezing improved together [1][2]. | [1][2] |
| Mechanism | Two circuits, two frequencies [4]. | [4] |
| Caution | Single-blind; programming-dependent [3][5]. | [3][5] |
Availability and limits
- This is an editorial summary of the publication, not a treatment recommendation [1][2].
- Requires a specific directional lead and device [3].
- Single-blind design; the definitive crossover trial is ongoing [5].
- Programming complexity limits transferability [3].
- Surgery carries the usual risks of intracranial electrode placement [4].
What to ask before booking
| Question | Why it matters |
|---|---|
| Is my freezing dopamine-responsive or resistant? | Resistant freezing is the indication for this strategy [4]. |
| Which electrode and device would be used? | Independent multi-target control requires specific hardware [3]. |
| Which department handles foreign patients, and in what language? | Xuanwu is a working hospital we do not book; confirm international-department coordination and language support. |
| How much programming follow-up is needed? | Dual-target settings require iterative adjustment [5]. |
Questions patients ask
What was tested?
Simultaneous high-frequency subthalamic and ultra-low-frequency (30 Hz) nigral stimulation using an eight-contact directional electrode, in a multicentre prospective single-blind study [1][3].
What was the result?
Both freezing of gait and limb motor symptoms improved significantly [1][2].
Why not just lower the frequency?
Low-frequency subthalamic stimulation helps gait but can cause limb symptoms to rebound; targeting two nuclei avoids that trade-off [1][4].
Where was it published?
Stereotactic and Functional Neurosurgery, online 19 January 2026 [1].
Is this relevant to international patients?
It is useful context for China's functional neurosurgery. Xuanwu is a working hospital we do not book — contact its international department directly [1].