
Quick answer
A peripheral lung nodule is easy to see on CT and hard to reach. Percutaneous biopsy risks pneumothorax, especially for nodules deep in the lung or far from the pleura; surgery removes the nodule but also removes lung. For a patient who has already lost lung to two operations, neither is attractive. Chen Enguo's respiratory team at Sir Run Run Shaw Hospital used a shape-sensing robotic bronchoscope to navigate to two nodules — one in each lung — biopsy them, and ablate them thermally, in a single 2.5-hour session. It was reported as a world first [1][2][4].
Key takeaways
- Patient: 65 years old, two prior lung nodule resections plus chemoradiotherapy, with growing bilateral ground-glass nodules [2][3].
- System: Ion shape-sensing robotic bronchoscopy, the first in Zhejiang province [1][2].
- Workflow: three-dimensional airway map built from the planning CT, with an AI algorithm proposing the optimal path [3].
- Outcome: both nodules biopsied and ablated in one session without a new incision [1].
- Programme volume: more than 130 robotic bronchoscopy procedures by mid-2025, after passing 100 in June [1][5].
Why reach is the limiting factor
Bronchoscopy can reach the central airways reliably; the further out a nodule sits, the more the bronchial tree branches, narrows and deforms with breathing. Shape sensing — fibre-optic tracking of the catheter's actual curvature — tells the operator where the instrument is rather than where it was predicted to be, which is what allows a peripheral target to be hit with confidence [2][3].
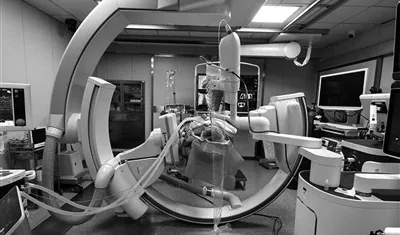
Treating both sides in one session is the practical gain. Two separate procedures mean two anaesthetics and two recovery periods for a patient with limited reserve; doing it once reduces the burden and the delay [1].
What a world-first case does not prove
The case demonstrates feasibility in a patient with no good alternative, and the department's 130-plus case volume indicates a real programme rather than a single demonstration [1][4].
No controlled data are reported on diagnostic yield, ablation completeness or recurrence compared with percutaneous or surgical approaches. Thermal ablation of a ground-glass opacity leaves the tissue in place, so follow-up imaging must establish that the nodule has been controlled — and ground-glass lesions can be multifocal and slow-growing, making long follow-up essential. Bronchoscopic ablation also requires general anaesthesia and a hybrid operating environment. The claim of a world first is about the combination of bilateral biopsy and ablation in one session, not about superiority [2][4].
The condition in context: pulmonary nodules
Low-dose CT screening and incidental imaging have made peripheral nodules a very common clinical problem.
| Region | What the data shows | Source |
|---|---|---|
| Dilemma | Most nodules are benign, but the ones that matter need tissue [2]. | SYSU/ZJU report [2] |
| Percutaneous limits | Deep or central lesions carry higher pneumothorax risk [3]. | Sohu report [3] |
| Surgical limits | Repeat resection sacrifices lung function [2]. | ZJU School of Medicine [2] |
Because the population screened is large and the majority of nodules are harmless, a tool that obtains tissue with less collateral damage has obvious value — if its accuracy holds [1][3].
Why it matters
| Potential | What the report suggests | Source |
|---|---|---|
| Access | Peripheral nodules reachable without a chest tube [2]. | [2] |
| Single session | Bilateral disease treated under one anaesthetic [1]. | [1] |
| Caution | Case-level evidence; ablation needs follow-up [4]. | [4] |
Availability and limits
- This is an editorial summary of hospital and press reporting, not a treatment recommendation [1][2].
- No comparative diagnostic yield or recurrence data [4].
- Requires a hybrid suite, anaesthesia and a trained team [2].
- Ablation is not equivalent to surgical resection [3].
- Long-term nodule control requires imaging surveillance, and bronchoscopic ablation is a recent addition to the department's practice [4][6].
What to ask before booking
| Question | Why it matters |
|---|---|
| How likely is my nodule to be malignant, and what is the pretest probability? | It determines whether biopsy is warranted [2]. |
| Is my nodule within reach of a bronchoscope? | Location decides the approach [3]. |
| Which department handles foreign patients, and in what language? | The hospital is a working hospital we do not book; confirm international-department coordination and language support. |
| How will the ablated nodule be followed? | Ablation leaves tissue that must be monitored [4]. |
Questions patients ask
What was done?
Two bilateral high-risk ground-glass nodules were biopsied and thermally ablated in a single 2.5-hour robotic bronchoscopy session using the Ion shape-sensing system [1][2].
Why was that notable?
The patient had already had two lung resections and could not tolerate a third, and treating both lungs in one session had not been reported before [1].
Is robotic bronchoscopy proven?
It is an established approach to peripheral nodules, but this report is a case, without comparative outcome data [4].
Does ablation replace surgery?
No — it is an option for patients who cannot tolerate resection, and requires surveillance [3].
Is this relevant to international patients?
It is useful context for China's interventional pulmonology. The hospital is a working hospital we do not book — contact its international department directly [1].