
Quick answer
Remote surgery has been technically possible for two decades; what has been missing is a network reliable enough to trust with a live operation. Sir Run Run Shaw Hospital in Hangzhou has built a programme around 5G and domestic robots that now includes operations on patients roughly 4,000 km away in Xinjiang, on three island patients in Zhoushan, and on a liver haemangioma controlled from Minsk during an exhibition — a distance of about 6,000 km. The programme is led by Cai Xiujun, the hospital's president [1][3][5].
Key takeaways
- Global firsts reported since 2023: 5G ultra-remote robotic cholecystectomy, liver resection, spleen-preserving distal pancreatectomy and transcontinental liver cancer surgery [3].
- January 2026: three island patients in Putuo, Zhoushan, operated remotely over two days — described as China's first multi-case remote robotic surgery in an island region [2].
- 27 January 2026: two consecutive remote liver resections by Liang Xiao, from Hangzhou to Shaoxing and then to Alar about 5,000 km away, with no reconfiguration between cases [4].
- August 2026: three consecutive remote partial liver resections to Alar in one day using a domestic robot with force feedback [1].
- The model is described as central-hospital expertise plus local collaboration, not remote control without a local team [3].
What makes it work technically
Three elements have to hold simultaneously: bandwidth and latency low enough for the surgeon's movements to feel immediate, a robot with enough dexterity and stability to execute them, and a local team able to manage the patient if the link fails. The last is the one that is rarely discussed and most important — every reported case had a full surgical team at the patient's side [3][4].
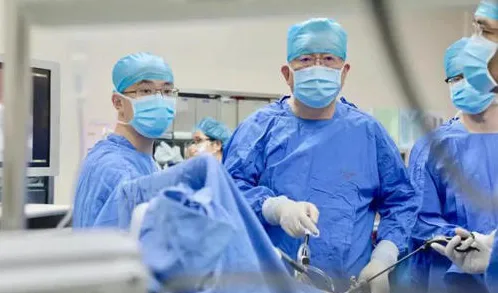
The consecutive-case design matters more than any single operation. Performing two or three complex hepatobiliary resections back-to-back, switching sites between cases, tests system stability and workflow rather than demonstrating a one-off stunt. The force-feedback robot used in the August 2026 series adds tactile information, which is the main sensory deficit in teleoperated surgery [1][4].
What this does and does not solve
The stated purpose is to move expertise rather than patients: a patient in Alar or on an island gets a hepatobiliary surgeon's judgement without a 4,000 km journey. For a liver resection, that is a genuine access problem, since complex hepatobiliary surgery is concentrated in major centres [3][5].
The reports describe technical success and system capability. They do not report complication rates, operative times or oncological outcomes compared with on-site surgery, and there is no randomised evidence for remote versus local operating. Cost is substantial: robot, network, redundant connections and two full teams. Whether the model is sustainable outside a flagship programme — and how it performs when the network degrades — are open questions. Regulatory frameworks for cross-province and cross-border responsibility are also still developing [1][4].
The condition in context: surgical access in China
China's specialist surgical capacity is concentrated in provincial capitals, while patients are spread across a very large country.
| Region | What the data shows | Source |
|---|---|---|
| Geography | Alar in Xinjiang is roughly 4,000–5,000 km from Hangzhou [1][4]. | Toudao / MicroPort [1][4] |
| Island access | Zhoushan's Putuo district requires sea transport for specialist care [2]. | SRRSH news [2] |
| Industrial context | Remote capability is cited by regulators as a strength of domestic surgical robots [3]. | Medical robot portal [3] |
Because the constraint is specialist availability rather than equipment alone, a network that carries expertise has more leverage than one that merely carries images [3].
Why it matters
| Potential | What the report suggests | Source |
|---|---|---|
| Access | Complex hepatobiliary surgery delivered locally [3][5]. | [3][5] |
| Repeatability | Consecutive cases across sites in one day [1][4]. | [1][4] |
| Caution | No comparative outcome data; high cost [4]. | [4] |
Availability and limits
- This is an editorial summary of hospital and industry reporting, not a treatment offer [1][2].
- No comparative outcome data against on-site surgery [4].
- Requires a local surgical team and reliable redundant connectivity [3].
- Regulatory and liability frameworks for cross-region surgery are evolving [5].
- Cost limits replication outside flagship centres, and sustainability beyond a flagship programme is unproven [1][6].
What to ask before booking
| Question | Why it matters |
|---|---|
| Who is physically present at my side during the operation? | A local team is the safety net [3]. |
| What happens if the connection fails mid-procedure? | Contingency planning is central to consent [4]. |
| Which department handles foreign patients, and in what language? | The hospital is a working hospital we do not book; confirm international-department coordination and language support. |
| Is there outcome data for remote versus on-site surgery here? | None has been published [4]. |
Questions patients ask
What has been done remotely?
Cholecystectomy, liver resection, spleen-preserving distal pancreatectomy, liver cancer surgery and a transcontinental liver haemangioma resection, mostly over 5G with domestic robots [1][3].
How far?
About 4,000–5,000 km to Alar in Xinjiang, and roughly 6,000 km from Minsk in one case [1][4].
Is it safe?
Reported cases were technically successful; comparative complication data are not published [4].
Who leads the programme?
Cai Xiujun, president of Sir Run Run Shaw Hospital and a hepatobiliary surgeon [1][3].
Is this relevant to international patients?
It is useful context for China's telemedicine capacity. The hospital is a working hospital we do not book — contact its international department directly [1].