
Quick answer
Remote surgery has been demonstrated for twenty years, but demonstrations are not evidence. The question a hospital board or a regulator asks is narrower: in a defined operation, with a defined network, is a remote operation as reliable as one performed at the bedside? Zhang Xu's urology team at PLA General Hospital ran a multicentre randomised trial across five Chinese centres to answer it. Remote robotic urological surgery was non-inferior to local surgery. The trial was published in The BMJ on 28 January 2026 [1][2][4].
Key takeaways
- Design: multicentre randomised controlled trial across five Chinese centres [1][4].
- Comparison: remote robotic urological surgery versus conventional local robotic surgery [2].
- Result: reliability of telesurgery was non-inferior to local surgery [1][3].
- First author Wang Ye of PLA General Hospital; co-first authors Xia Dan (Zhejiang University First Affiliated Hospital), Mulati Rexiati (Xinjiang Medical University First Affiliated Hospital) and Zhao Wuyi (Edge Medical) [2].
- Corresponding authors: Zhang Xu, Li Hongzhao and Ma Xin of PLA General Hospital, with Liang Chaozhao of Anhui Medical University First Affiliated Hospital [2].
What "reliability" means here
A telesurgery trial cannot be designed like a drug trial. The interesting failure modes are technical: latency, packet loss, instrument lag, and the coordination between a remote console and a local bedside team. The trial therefore assessed whether the operation could be completed reliably under remote control, not merely whether patients recovered [2][4].
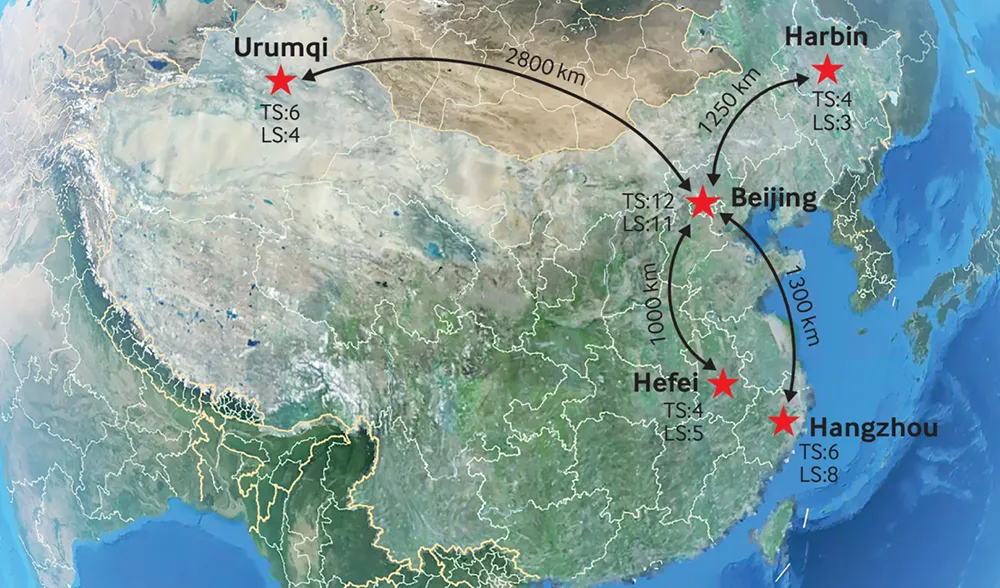
The programme behind it is long. Zhang's group describes more than a decade of work running from robot development through preclinical animal studies and exploratory clinical cases to this multicentre randomised trial — the sequence a device needs before a regulator or a payer will take it seriously [2][5].
What the trial does not settle
Non-inferiority in a controlled trial is a starting point, not an endpoint. It says that under the conditions tested, remote operation did not perform measurably worse [1][4].
The trial necessarily used procedures suited to remote operation and networks engineered for it; results do not automatically transfer to emergency surgery, unstable patients, or ordinary commercial internet. Cost is not addressed — a remote programme requires robots at both ends, redundant high-bandwidth links and two clinical teams. The published reports available here do not give the sample size or the numeric between-group differences, so the margin within which non-inferiority was declared should be read in the paper itself [3][4].
The condition in context: access to robotic urology
Robotic surgery for prostate, kidney and bladder cancer is concentrated in major centres, and telesurgery is proposed as a way to distribute it.
| Region | What the data shows | Source |
|---|---|---|
| Constraint | Traditional surgery requires surgeon and patient in the same physical space [2]. | CUA [2] |
| Potential beneficiaries | Remote regions, disaster and military settings, and space missions are the stated use cases [2]. | CUA [2] |
| Domestic platforms | Chinese robotic systems have been used for remote procedures across thousands of kilometres [3]. | NetEase [3] |
Because urology is one of the highest-volume robotic specialties, proving reliability there has more practical consequence than in a rare operation [1].
Why it matters
| Potential | What the report suggests | Source |
|---|---|---|
| Evidence level | First randomised evidence for telesurgery [1][3]. | [1][3] |
| Reach | A basis for scaling remote programmes [4]. | [4] |
| Caution | Specific operations and networks; cost unaddressed [4]. | [4] |
Availability and limits
- This is an editorial summary of the publication, not a treatment recommendation [1][2].
- Results apply to the procedures and networks studied [4].
- A local surgical team and redundant connectivity remain mandatory [2].
- Cost-effectiveness and regulatory frameworks for cross-region practice are unresolved [3].
- Long-term functional and oncological outcomes are not reported here [4].
What to ask before booking
| Question | Why it matters |
|---|---|
| Which specific operation was validated remotely? | Non-inferiority applies to those procedures [4]. |
| Who is at my bedside during the operation? | The local team is the fallback [2]. |
| Which department handles foreign patients, and in what language? | PLA General Hospital is a working hospital we do not book; confirm international-department coordination and language support. |
| What is the contingency if the network fails? | It must be part of consent [3]. |
Questions patients ask
What was tested?
Remote robotic urological surgery versus conventional local robotic surgery in a multicentre randomised controlled trial across five Chinese centres [1][4].
What was the result?
Telesurgery was non-inferior to local surgery on the trial's reliability measures [1][3].
Why is it notable?
It is described as the first randomised controlled trial of telesurgery [1][3].
Where was it published?
The BMJ, online 28 January 2026 [1][2].
Is this relevant to international patients?
It is useful context for China's surgical robotics. PLA General Hospital is a working hospital we do not book — contact its international department directly [1].